

Eighteen months after his diagnosis, chemotherapy had failed to slow 21-year-old Mason Henderson’s rare brain tumor, which had spread into his spinal fluid. With few options left, he traveled from southeastern Texas to New York City for a three-week clinical trial.
That treatment failed as well, leaving Henderson and his family facing an uncertain future. His cancer was so uncommon that the World Health Organization had only named the disease in 2021. Early this year, after examining the tumor’s genetic profile, his doctors turned to Lynparza, a drug manufactured by Merck and AstraZeneca.
Lynparza was not an established treatment for Henderson’s cancer. In fact, there was no recognized standard of care, a situation that is common with rare tumors. Despite detailed medical explanations from the two specialists treating him, Henderson’s insurer refused to cover the drug.
“They have no guidelines for his cancer,” Henderson’s mother, Tabitha Lowe, said in a March interview with KFF Health News. “They’re discriminating against him because his cancer is so rare.”
Each year, tens of thousands of Americans — roughly one-quarter of all cancer patients in the United States — receive diagnoses involving tumors considered rare because they differ significantly from more common cancers. When deciding whether to pay for treatment, insurers typically rely on Food and Drug Administration approvals and widely accepted clinical guidelines.
The problem is that rare cancers frequently have no targeted therapies approved by the FDA. Yet molecular testing performed by commercial diagnostic companies and university laboratories can sometimes offer compelling evidence about which medicines may help.
“Insurance coverage routinely trails behind what genomic testing reveals about a patient’s cancer and what the science supports,” said Olivier Elemento, director of Weill Cornell Medicine’s Englander Institute for Precision Medicine.
Henderson’s neuro-oncologists, Jacob Mandel of Baylor College of Medicine and Jessica Schulte of NYU Langone Health, recommended Lynparza — also known as olaparib — alongside chemotherapy. The evidence was limited, but Schulte said the decision was “biologically reasonable.” Tumors like Henderson’s carry a cellular defect that drugs such as Lynparza may exploit, and doctors had previously seen similar brain cancers respond to the medication.

Tabitha Lowe
“In general, we try to base our treatment decisions on large patient studies” involving hundreds of people, Schulte said. But a major clinical trial is unlikely ever to be conducted for a cancer as rare as Henderson’s.
Schulte, who treats brain cancers in young adults, said she encounters only a handful of patients with Henderson’s diagnosis each year.
Mandel prescribed Lynparza on Jan. 16. Liviniti, Henderson’s pharmacy benefit manager, rejected the request two weeks later, on Jan. 30. The company followed up with a written explanation: “Lynparza is not approved for the diagnosis provided.” Without insurance coverage, the medication would cost about $8,700 a month, Lowe said. Liviniti did not respond to phone calls requesting comment.
Before becoming ill, Henderson was a healthy, athletic young man known for his generosity, Christian faith and close-knit circle of friends, his mother said. At Evadale High School, north of Beaumont, Texas, he played baseball and football and was named homecoming king in 2022. After graduation, he worked at the area paper mill and spent his spare time hunting, fishing and riding an all-terrain vehicle through the woods. He hoped to become a police officer, Lowe said.
Henderson was 20 on March 15, 2024, when his brother, Gunner, discovered him sitting at the top of the stairs at their family home with his head in his hands. “He was in the post-seizure state,” Lowe said. “He couldn’t talk. Was crying. Trying to hug me. Could not communicate.”
Doctors at an emergency room in Beaumont performed an MRI and found a large tumor. Henderson was transferred to Baylor St. Luke’s Medical Center in Houston, where he was diagnosed with diffuse hemispheric glioma (H3 G34-mutant), a rare form of brain cancer.
Surgeons removed about 90% of the tumor several days later. But completely eliminating a brain tumor is often impossible because of the sensitive tissue surrounding and containing it, Schulte said.
After 16 months of radiation and chemotherapy, a scan in September 2025 showed that the cancer had reached Henderson’s spinal cord. The spread, known as leptomeningeal disease, is typically fatal within months. Mandel then contacted Schulte about a clinical trial she was leading. The trial involved 11 days of intense craniospinal radiation, leaving Henderson severely exhausted. When the treatment ended, however, the cancer remained.
“The family was wonderful,” Schulte recalled. “They were trusting in their team, but they asked appropriate questions to make sure that we were thinking about Mason as a person.”
Coverage refused
The FDA approved Lynparza in 2014 for ovarian cancer. The drug works by disrupting cancer cells’ ability to reproduce. After Liviniti denied coverage, Henderson’s family sought help from Jefferson County, where his stepfather, Jerry Lowe, works as a helicopter pilot for the county sheriff’s office.
Because Jefferson County directly pays claims for health coverage provided to employees’ families, it had the final authority over reimbursement. The county also rejected the request. After the family appealed, a county review board arranged for an independent medical reviewer to assess the case. The reviewer, who was not a specialist, upheld the denial and recommended a different drug. Henderson’s physicians disagreed. The board did not respond to a request for comment.
AstraZeneca also rejected the family’s request for a donated supply of Lynparza. By then, it was March — six weeks after the drug had been prescribed.
Cancers that start in the brain are unusual — only about 25,000 cases are diagnosed in the U.S. each year, compared with 320,000 breast cancers and 229,000 lung cancers. Only a few hundred people each year, mostly young adults, are diagnosed with Henderson’s type, according to Schulte.
Treatment options for diffuse hemispheric glioma are few; brain cancers in general are often excluded from clinical trials. They represent a relatively small market for a pharmaceutical company. Testing drugs against them is risky, because of the brain’s sensitivity, and difficult because the drug must pass through the tightly packed cell walls lining the blood vessels, known as the blood-brain barrier.
Still, drugmakers are increasingly homing in on narrower and potentially more accurate drug targets as science reveals more of cancer’s remarkable molecular diversity.
Under guidance issued in 2022, the FDA has approved nine drugs to be used for patients whose tumors have specific mutations, regardless of the organ where the cancer first appeared. These “tissue agnostic” drugs are still a tiny minority, but as genome sequencing becomes more common — growing numbers of oncologists order it for patients — insurers will have to keep up, Weill Cornell’s Elemento said.
Several U.S. research groups are hosting clinical experiments known as “basket trials,” in which mostly late-stage cancer patients are put on drug combinations based on tumor genetics, rather than the organ of origin.
The American Society of Clinical Oncology has recruited more than 3,000 patients into one of the biggest efforts, the Targeting Agent and Profiling Utilization Registry, or TAPUR, which began in 2016. It provides off-label treatments at no cost to advanced-staged cancer patients at more than 270 U.S. oncology practices.
About half the participants have benefited, and in rare cases the treatment kept patients alive for a year or more or seemingly cured them, said Richard Schilsky, the program’s founder and its principal investigator until recently. The results have led to changes in several treatment guidelines, he said, and a change in guidelines “usually is sufficient to create a pathway to reimbursement by insurance.”
Research has uncovered “quite a few” cases in which Lynparza was effective against a variety of tumor types, Schilsky said. But like many clinical trials, TAPUR excludes patients with primary brain tumors — like Henderson’s.
Oncologists disagree on how broadly genetics discoveries will transform cancer diagnosis. Cancers are currently identified as breast, colon, lung, etc., because those are the cells that pathologists see when diagnosing a tumor, said Razelle Kurzrock, the associate director of clinical research at the Medical College of Wisconsin Cancer Center.
But that’s a “mistake of history,” she said. “You’re making the diagnosis based on the pathologist’s view of the surface of the cell rather than what’s actually driving the cancer.”
A Dutch father and son invented the first light microscope to peer at cells around 1590. The Human Genome Project finished in 2003. If genome-enabled next-generation sequencing, now used for molecular tumor scans, had come before the light microscope, “no one would look at organ of origin,” she said.
Kurzrock leads I-PREDICT, a clinical trial in which every patient gets individualized cancer therapy based on DNA, RNA, and protein patterns in their tumor. Instead of getting drug combination A or B, “in our trial everyone gets a different set of drugs,” she said. Physicians can instead use standard therapies, she said, and their patients are the study controls.
Other oncologists see limitations to purely genetic diagnosis. Certain cancer centers advertise by saying, “‘We’ll sequence your tumor better than anyone else, and therefore you’ll live longer and do better if you come here,'” said Kathy Miller, a professor of oncology at Indiana University. “But the evidence doesn’t support those claims right now.”
“I wouldn’t give up”
In Henderson’s case, the problem was never diagnosis; Baylor clinicians identified his cancer type quickly. But its rarity and location made the tumor hard to fight, and the lack of financial help made it even harder.
On March 8, Tabitha Lowe went on Facebook, LinkedIn, and Instagram with photos of her son and descriptions of his plight. She tagged AstraZeneca, Liviniti, and the county board that had denied his reimbursement. “Rare cancer patients are denied treatment simply because their cancers are rare,” she wrote in one of the posts, which were shared hundreds of times.
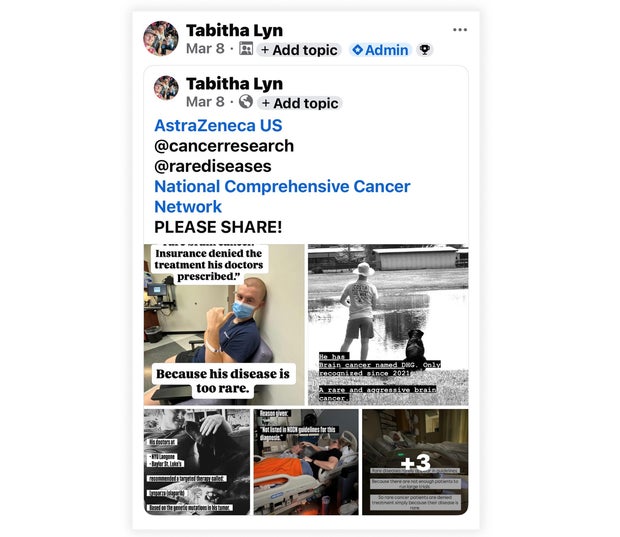
Tabitha Lowe
“I hated to take this route, but when it comes to my kids there’s nothing I won’t do,” she told KFF Health News. “I’ve cried, I’ve stressed out, but I wouldn’t give up.”
The next day, AstraZeneca’s patient assistance program, which had turned down her request for the drug two weeks earlier, emailed her with good news: A bottle of 60 Lynparza pills had been shipped to her pharmacy. Company spokesperson Tara Parsell said patient confidentiality prevented her from commenting on its actions.
Lowe’s six-week battle had paid off. Now, “it’s in God’s hands,” she said in an April interview. By mid-April, however, Henderson could no longer walk. Then came issues with his speech. “It all happened so fast.”
On May 4, in the family’s living room, where his bed had been moved, Henderson died, after taking the drug for nearly two months. Hundreds attended his memorial service; their cars made a procession seven minutes long.
The family has created a college scholarship in Henderson’s name for graduates of the local high school. An online campaign and bass fishing tournament had raised nearly $24,000 by September. Willie Robertson of Duck Dynasty, professional pickleballer Tyson McGuffin, and pro fisherman Hank Parker donated items for a raffle. Country singer Mark Chestnutt sent two signed guitars, Lowe said.
“Faster treatment would have been better,” although it’s hard to know whether it would have extended Henderson’s life, NYU’s Schulte said.
“I will always wonder,” Lowe said in a phone interview this summer. “Cancer don’t pause while the paperwork’s in progress.”
“There’s something especially painful thinking about how much time I spent fighting healthcare instead of being with Mason,” she added. “I was forced to become a PBM, insurer, research expert, all while trying to be his mother.”
KFF Health News is a national newsroom that produces in-depth journalism about health issues and is one of the core operating programs at KFF — the independent source for health policy research, polling, and journalism.















